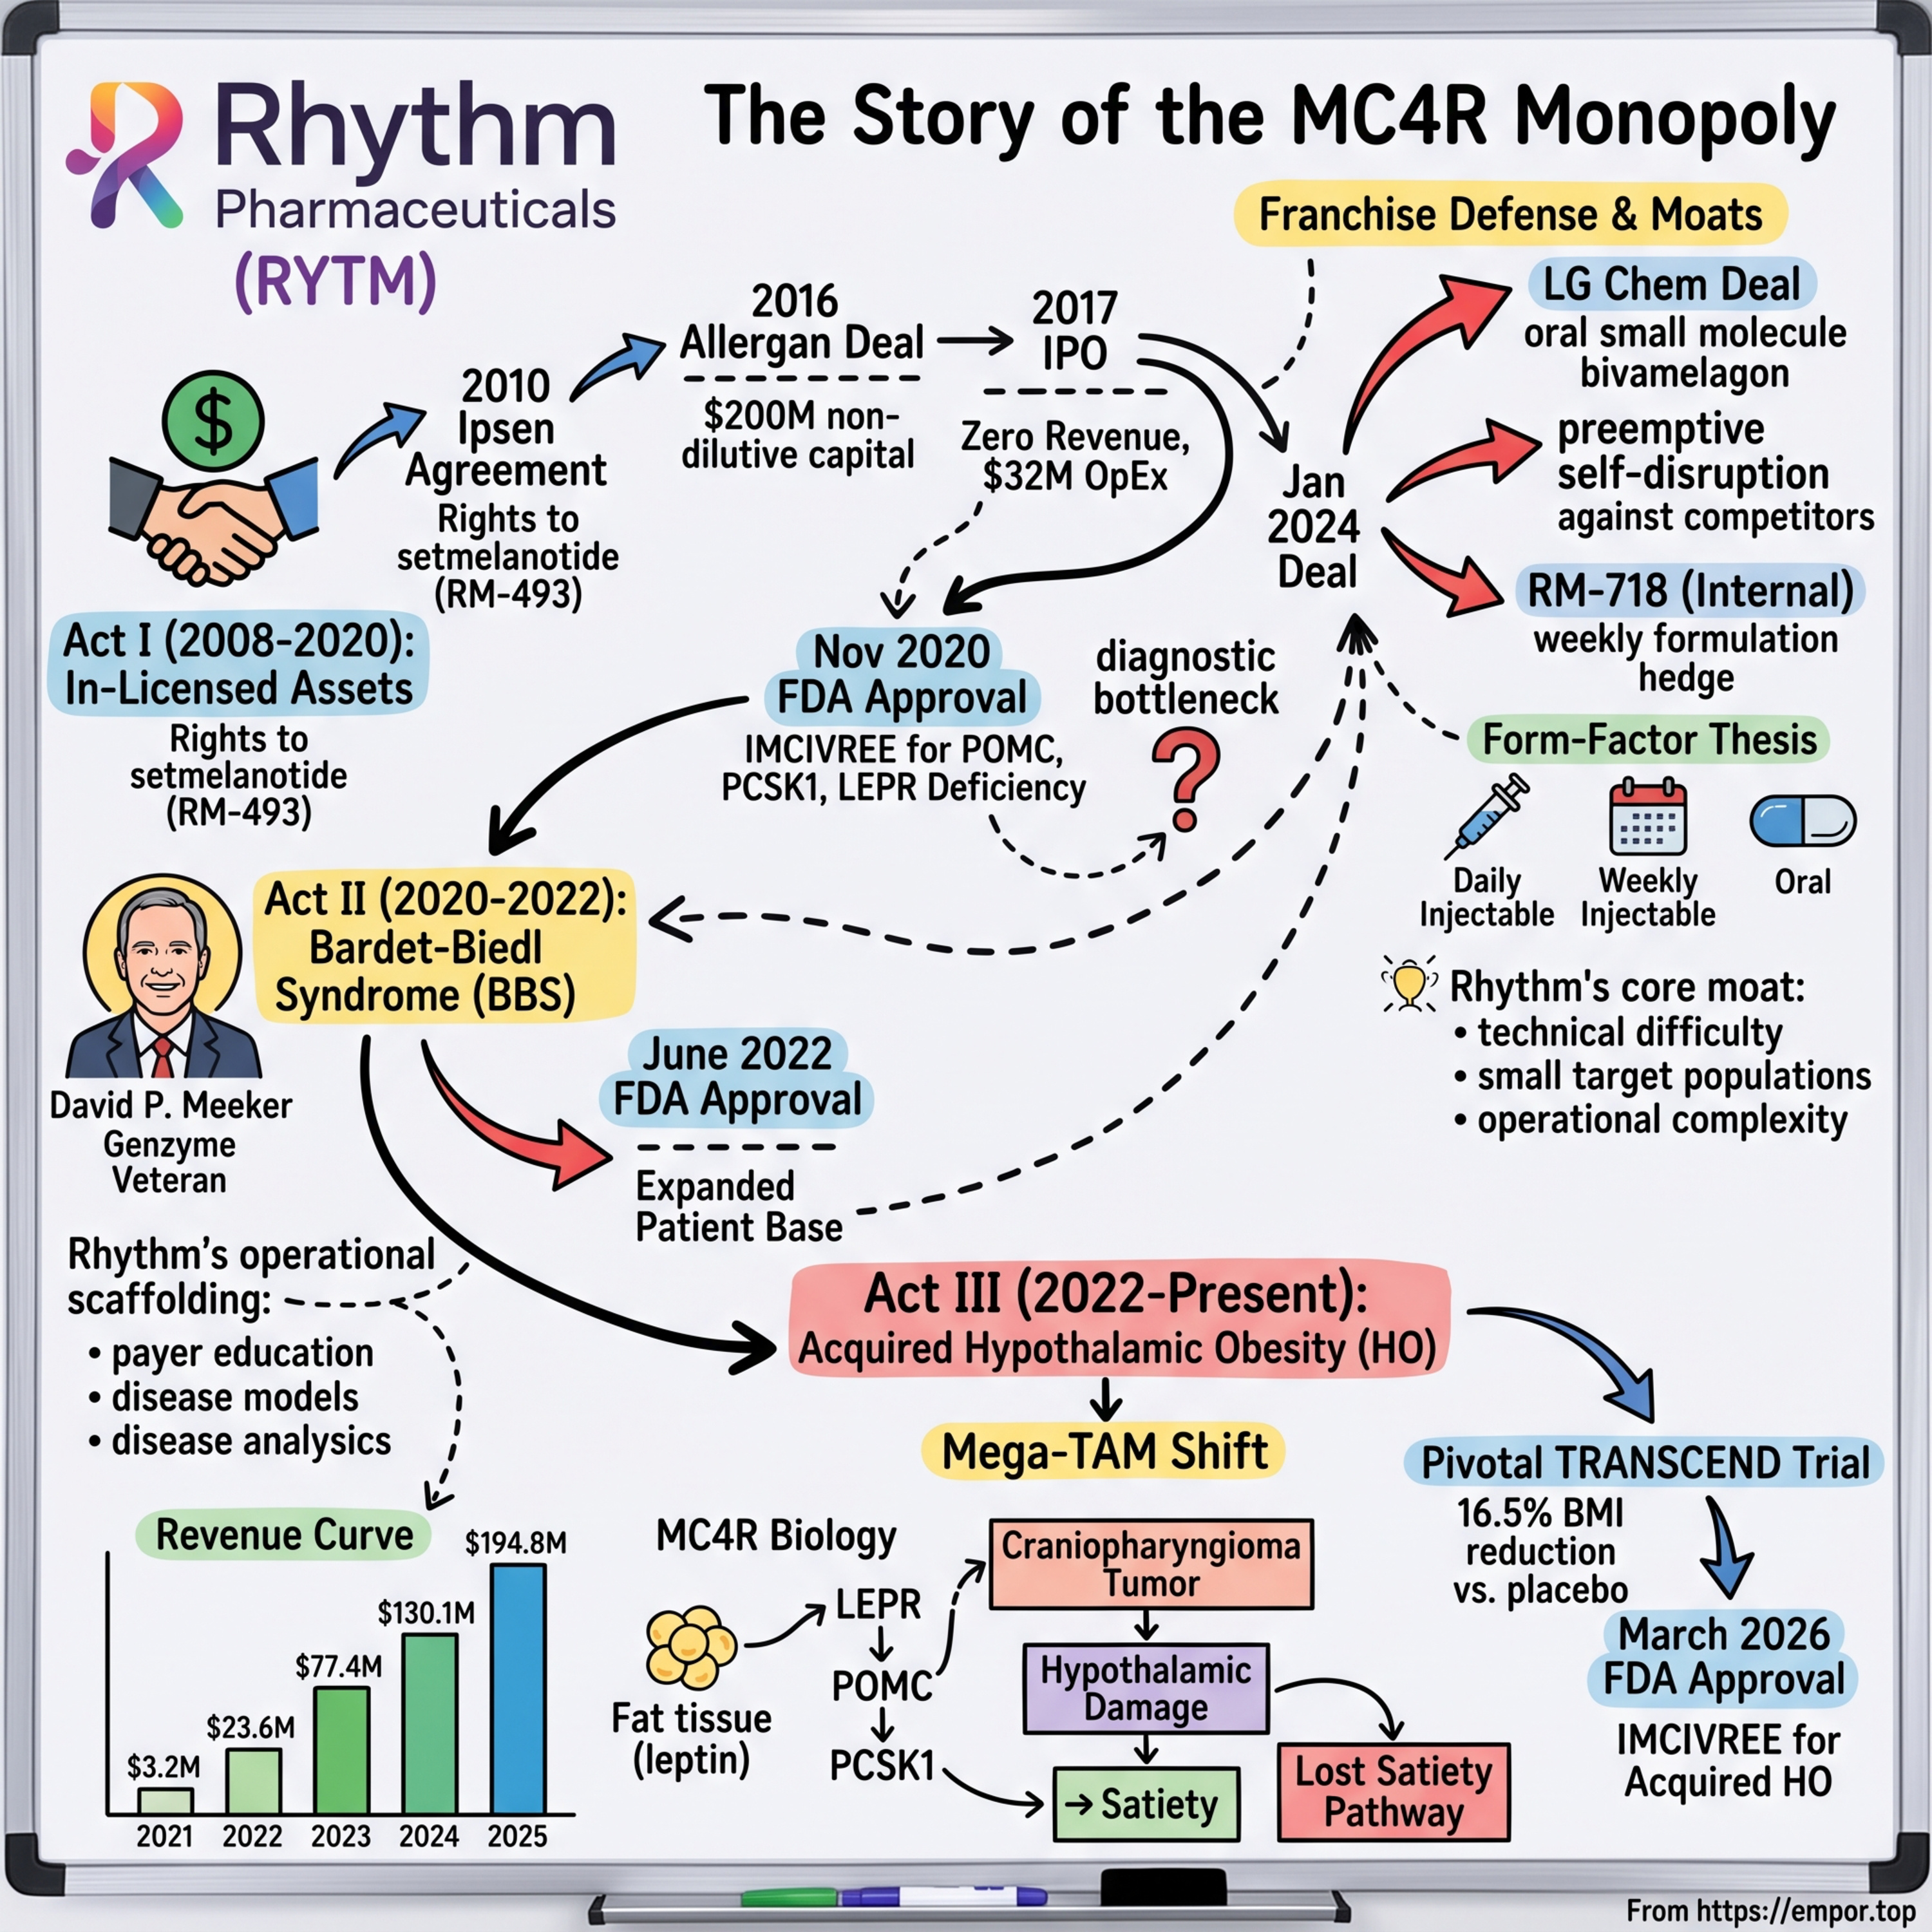
Rhythm Pharmaceuticals: The Story of the MC4R Monopoly - $RYTM
from Empor.top - The Stories of Top Companies
79m 54s
Rhythm Pharmaceuticals has established a niche in the rare disease space by targeting obesity caused by disruptions in the melanocortin IV (MC4R) receptor pathway. Its flagship therapy, imcivry, received FDA approval for rare genetic disorders like POMC and PCSK1 deficiencies in 2020, and later for acquired hypothalamic obesity in 2026, expanding its addressable market from a few hundred to tens of thousands of patients globally. The company’s strategy hinges on identifying patients through diagnostic programs, building strong physician and medical center relationships, and securing payer reimbursement by framing the condition as a distinct neuroendocrine disease rather than elective weight loss. Despite strong gross margins—nearly 90% and a high gross-to-net realization rate of 84%—Rhythm remains unprofitable, with operating expenses rising 35% in 2026 due to expanded commercial and clinical infrastructure. A key defensive move was acquiring LG Chem’s oral MC4R agonist to preempt competitive displacement. Additionally, Rhythm is developing a next-generation peptide (RM718) to eliminate skin hyperpigmentation and a new oral formulation to diversify its pipeline. However, the path to profitability is uncertain, as revenue growth depends on patient conversion rates, reimbursement timelines, and sustained payer acceptance. Investors must assess whether Rhythm can maintain its commercial moat in the face of broader market competition, operational complexity, and the inherent challenges of ultra-rare disease commercialization. The company’s success underscores that rare disease value is not just in science, but in diagnosing, managing, and positioning a disease as medically necessary—work that requires long-term, relationship-intensive execution.
This podcast is brought to you by mpoor.top, the stories of top companies.
Disclaimer, this AI-generated content is for informational purposes only and should
not be considered as investment advice.
If you like our podcasts, please subscribe on Apple Podcasts, Spotify, or your favorite
podcast player, and don't forget to follow us on X at mpoor.top.
Find thousands of stories of top companies on our website mpoor.top.
mpoor.top is brought to you by hayfin.co.
Fin is a personalized junior AI research assistant for equity portfolio managers.
Check it out at hayfin.co.
Rhythm Pharmaceuticals, the story of the MC4R monopoly.
On March 19, 2026, a commercial team in Boston received the regulatory decision every rare
disease developer targets for years.
The US Food and Drug Administration approved imcivary set melanatide to reduce excess body
weight and maintain reduction long-term in adults and pediatric patients aged four years
and older with acquired hypothalamic obesity.
The context surrounding that regulatory milestone is striking, while the pharmaceutical industry's
primary narrative focused on a massive race between Eli Lilly and Novo Nordisk to market
in-cretan therapies to tens of millions of patients, a biotech firm with roughly 68 million
shares outstanding and under $200 million in annual revenue secured the first approval
in history for a disease that most endocrinologists could not have defined a decade earlier.
The core thesis Rhythm Pharmaceuticals, RYTM, is built on the premise that a single biological
circuit, the melanocortin IV receptor MC4R pathway, represents a defensible commercial
domain rather than a scientific specialty.
The company's strategy centers entirely on that pathway, from the assets it inlicensed
and the indications it pursued to the specialized Salesforce it deployed and the pipeline compounds
it acquired to safeguard its franchise.
Management's thesis is that Rhythm controls the only approved therapy to address this
specific disruption in hypothalamic signaling.
For investors, the central task is evaluating how much of that position reflects an enduring
monopoly, how much is a temporary regulatory lead, and how much represents the standard
risks of a loss-making biotech that has yet to demonstrate it can convert scientific breakthroughs
into durable cash flows.
That financial context is critical.
Through the end of 2025, Rhythm had never achieved profitability.
The company consumed approximately $116 million in operating cash in 2025 alone and closed
the year with roughly $389 million on its balance sheet.
Rhythm's enterprise value ultimately depends on its commercial execution rather than historical
earnings.
The obesity industry's blind spot.
The rapid rise of GLP-1 therapies created a distinct market asymmetry.
While flooded into treatments designed to reduce appetite in general patient populations,
while far fewer resources reached individuals whose hunger stems from severe structural
or genetic disruptions, patients whose brains cannot register satiety because of tumor,
surgery, radiation, or an inherited genetic defect severed the neural pathway.
In clinical terms, this condition is hyperphagia, not standard appetite or food cravings, but
an unrelenting physiological state in which the brain registers continuous starvation.
Rhythm wagered that this patient population constitutes a distinct rare disease market with
favorable orphan drug economics, rather than a small subset destined to be displaced
by broader, lower-cost, in-cretin drugs.
The product, Imsivri, is a daily subcutaneous injection of set melanatide, a peptide engineered
to bind directly to the MC4-R receptor.
When upstream signaling is disrupted by genetic mutations or physical damage to hypothalamic
tissue, set melanatide acts as a substitute activator at the target receptor.
That mechanism highlights both the drug's therapeutic precision and its core limitation.
The underlying MC4-R receptor itself must remain intact and functional.
REE acts. Act 1, 2008, 2020.
Inlicensed assets, a corporate split, an initial public offering, and the initial approval
for obesity resulting from POMC, PCSK1, or LEPR deficiency.
A scientific landmark accompanied by a commercially narrow patient population.
Act 2, 2020, 2022.
The appointment of chief executive officer, Dr. David P. Meeker, a veteran rare disease
executive from Santa Fe, Genzyme, followed by the June 2022 approval in Bardet, Beetlesindrome,
that provided rhythm its initial commercial revenue base.
Act 3, 2022.
Present.
The strategic pivot to acquired hypothalamic obesity, an estimated target population of 10,000
patients in the United States, a similar cohort in Europe, and 5,000 to 8,000 in Japan,
which represents the primary driver of the company's valuation.
What this episode covers?
This section previews the key dynamics shaping the company.
MC4-R biology versus Incritin biology, and the commercial implications of that distinction.
The Ipsin license that provided rhythms founding asset at minimal upfront cost.
The execution of Meeker's rare disease strategy, and the unit economics of therapies priced
above $300,000 annually per patient.
It also details rhythms life cycle defense initiatives, including an oral small molecule
acquired from LG Chem, and an internally developed weekly peptide.
Alongside crucial stress tests, such as the Phase 3 MNAT trial failure in March 2026,
and underwhelming Prader-Willy syndrome data in June 2026.
Analyzing rhythm requires examining more than its balance sheet.
It begins with the neural circuits governing human energy homeostasis.
On the fourth quarter 2025 earnings call, rhythms head of North America described a conversation
between a company field representative and an endocrinologist.
The physician was managing a patient who had gained severe weight following treatment
for a brain tumor, subsequently underwent gastric bypass surgery, and later started a
GLP-1 receptor agonist.
With, in the executive's words, minimal benefit.
That case compresses the company's core commercial premise into a single patient history.
Two of the most aggressive weight loss interventions in modern medicine, bariatric surgery and Incritin
therapy, failed because neither restored the damaged neural pathway responsible for
satiety signaling.
The circuit, in plain terms, the neural control of satiety functions like a four-stage relay
in the hypothalamus.
One, fat tissue secretes leptin, a hormone signaling stored energy reserves.
Two, leptin binds to its receptor, LEPR, on a targeted set of neurons.
Three, those neurons produce a precursor protein, POMC.
Four, an enzyme, PCSK1, cleaves POMC into alpha MSH, a peptide that binds MC4R on downstream
neurons.
That binding delivers the critical signal.
Energy reserves are sufficient, stop eating.
Interrupting any stage of this signaling chain prevents the satiety message from reaching
its destination.
The brain interprets this absence of signal as continuous starvation and responds accordingly.
Hyperphagia is not a failure of behavioral willpower, but a chronic physiological signaling
defect that overpowers voluntary regulation.
The practical reality of this condition directly drives therapy adherence.
Rhythm's commercial team highlighted the case of a Bardet Beetle syndrome patient in an
assisted living facility whose fixation on food was severe enough to prevent participation
in group activities.
In six months of initiating set melanotype therapy, the patient lost approximately 40 pounds
and resumed social activities.
Caregivers of patients with severe hyperphagia routinely report keeping pantries and refrigerators
locked to prevent night eating.
For these families, the primary therapeutic milestone is not merely weight loss, but the
reduction of persistent hunger signals.
For investors, this clinical dynamic creates distinct adherence economics.
A drug that addresses a symptom around which families restructure daily routines is rarely
discontinued for convenience.
Discontinuations are predominantly driven by tolerability issues or reimbursement barriers,
neither of which reflects an underlying lack of patient demand.
A second mechanism can break the melanocortin pathway, presenting a broader commercial opportunity.
When a cranioferin geoma, a benign tumor located near the pituitary gland, is surgically
resected or irradiated, the hypothalamic neurons themselves can be permanently destroyed.
Even when the underlying genes remain intact, the physical hardware is lost.
The resulting weight gain is rapid, severe, and largely resistant to standard dietary,
lifestyle, or hormone replacement interventions.
Why in credence do not solve this?
GOP1 and GOP2
IP receptor agonists operate primarily through gut signaling, vagal pathways, and appetite
centers located upstream of, or parallel, to the melanocortin circuit.
When the target MC4R receptor remains functional, but upstream signaling is absent, a direct MC4R
agonist can restore the satiety signal.
Conversely, if an in-credent therapy attempts to stimulate a pathway that relies on destroyed
hypothelamic tissue to process its signal, the intervention yields minimal effect.
Rhythm has not published head-to-head clinical trial data comparing set melanatide directly
against GLP1 therapies in hypothelamic obesity.
Consequently, claims regarding GLP1 refractoriness in this population rely on biological mechanism,
clinical observations, and physician reports, rather than randomized comparative data.
However, placebo data from the Phase III Transcend trial is informative.
Control-arm patients gained body mass index over 52 weeks, despite receiving standard medical
care.
In this population, conventional interventions failed to arrest disease progression.
Why nobody else got here first?
Developing selective MC4R agonists has historically proven difficult.
The melanocortin receptor family includes closely-related subtypes.
MC1R regulates skin pigmentation, while other subtypes modulate cardiovascular function.
Previous drug candidates targeting MC4R induced blood pressure elevations that precluded
chronic administration.
Set melanatide avoided significant cardiovascular toxicity, but it did not eliminate off-target
melanocortin effects entirely.
The FDA prescribing information for acquired hypothelamic obesity notes that skin hyperpigmentation
occurred in a majority of clinical trial participants.
Depression and suicidal ideation require routine monitoring, and approximately 5% of patients
experienced acute adrenal insufficiency.
The initial 2020 regulatory label also included warnings regarding altered sexual arousal and
hyperpigmented Nevi.
These side effects carry practical commercial implications.
skin hyperpigmentation prompted rhythm to initiate development of a next-generation peptide engineered
for greater MC1R selectivity, and the adverse effect was cited when a trial participant
in Japan discontinued therapy during the Transcend study.
A competitive mode grounded in the difficulty of manufacturing a selective molecule offers
protection, but it also reflects the limitations of the initial asset.
The economics of a very small market, orphan drug economics invert standard pharmaceutical
commercial models.
Instead of serving large patient populations at lower prices, orphan drug models depend
on treating small patient populations at premium prices.
Published health technology assessment analyses estimate the annual treatment cost for set
melanatide at approximately $294,000 for pediatric patients and $441,000 for adults receiving
the maximum labeled dose.
Rhythm's financial disclosures reflect these unit economics.
Cost of goods sold represented 11.9% of product revenue in the first quarter of 2026 and
8.5% in the fourth quarter of 2025.
Figures that include ongoing royalty obligations owed to Ipsin.
Because peptide manufacturing costs remain low, realized gross margins are primarily determined
by market exclusivity and pricing power rather than underlying production costs.
A key commercial metric is the company's gross to net realization rate, which reached
roughly 84% in the first quarter of 2026 and 84.6% in the fourth quarter of 2025.
Rhythm retained approximately 84 cents of every list price dollar after accounting for mandatory
rebates, commercial discounts, and patient copay assistance.
This high realization rate indicates limited pricing resistance from commercial payers
to date.
However, this metric faces potential pressure as the patient mix expands into Medicaid
programs and as European health systems finalize national reimbursement terms.
The barrier that is not a patent rare disease commercial franchises are often protected
less by patent barriers than by structural hurdles to market entry establishing a competing
therapy in acquired hypothalamic obesity requires clearing several distinct operational hurdles.
Developing a molecule with demonstrated MC4R selectivity that avoids cardiovascular
safety signals, a technical hurdle that repeatedly stalled earlier industry development programs.
Conducting a randomized clinical trial in a diagnosed population limited to a few thousand
patients globally, now complicated by the presence of an approved therapy that makes
placebo controlled enrollment difficult.
Satisfying regulatory requirements for a 52 week primary endpoint to measure weight trajectories
in a slow progressing condition.
Deploying a specialized commercial field force to identify patients who lack standardized
diagnostic coding and are scattered across multiple medical specialties.
Individually these challenges are manageable.
Together they require five to seven years of development and significant capital expenditure
for a target population that major pharmaceutical companies may view as commercially modest.
This dynamic, high clinical and operational complexity relative to absolute market size,
forms rhythms primary commercial moat, however that protection endures only so long as the
market remains unappealing to larger industry competitors.
The structural question facing rhythm is whether a sustainable commercial enterprise can
be built on a patient population of this scale.
An objective the company's initial strategy struggled to achieve, rhythm did not begin
with an in-house scientific breakthrough.
It began with an asset acquisition.
The company was organized in 2008 as a subsidiary of Rhythm Holding Company LLC, a vehicle backed
by venture firms MPM Capital and new enterprise associates to build around assets it did not
invent.
Rather than spending a decade discovering new molecules, the founding strategy relied
on acquiring two clinical stage peptides from a large pharmaceutical company and identifying
commercially viable indications for them.
The Ipsen Bargain In February 2010, the predecessor company entered
into a licensing agreement with Ipsen Pharma SAS, acquiring worldwide rights to two clinical
candidates, set Melanitide, then designated RM493, an MC4R agonist, and Rela Morellen,
RM131, a Grellen agonist.
Contemporaneous industry reporting estimated the total potential value of the arrangement
across both programs at up to $80 million.
The set Melanitide specific terms disclosed in Rhythm's SEC registration statement were modest
relative to typical biotech licensing deals.
Aggregate development and commercial milestones were capped in the tens of millions of dollars
alongside mid-single-digit royalties on future sales.
Rhythm was still paying that royalty 15 years later, making it a persistent line item
in cost of goods sold through 2025.
In 2010, Ipsen viewed set Melanitide as a broad obesity asset in a receptor class known
for cardiovascular safety challenges during an era when major drug makers were scaling
back investments in general weight loss therapies.
For Rhythm, the transaction demonstrated a core thesis.
Commercial value was created not in the deal itself, but in subsequently narrowing the
target population until the drug demonstrated clear clinical benefit.
The split that funded everything.
By the mid-2010s, Rhythm's two licensed assets served distinct clinical markets.
Rela Morellen was being developed for diabetic gastroparesis within gastroenterology, while
set Melanitide was targeted toward rare genetic disorders of the Melano-Cortin pathway.
Management chose to separate the assets rather than build parallel commercial capabilities.
Rela Morellen was placed into a subsidiary, Modus Therapeutics, and in October 2016, allergen
exercised an option to acquire Modus for $200 million.
The proceeds returned to the Rhythm holding structure, providing non-dilutive capital that
funded set Melanitide's transition into rare genetic obesity.
By divesting its gastroenterology candidate, the pre-revenue biotech secured nine figures
in capital without executing a dilutive equity round.
That transaction established an early corporate pattern, prioritizing resource concentration
in rare disease over portfolio breadth.
During this period, Rhythm also pursued formulation alternatives, licensing cameras' fluid crystal
delivery technology in January 2016 to evaluate a long-acting formulation of set Melanitide.
While that specific program did not yield a commercial product, it reflected early efforts
to explore asset life-cycle options.
The 2017 IPO
Rhythm completed its initial public offering in October 2017, pricing 8,107,500 shares
at $17 per share to raise roughly $138 million in gross proceeds.
The company entered the public markets as a clinical stage entity with zero revenue and
annual operating expenses of a person.
approximately $32 million in 2017.
The offering funded registration trials
to test a specific clinical hypothesis.
Early data indicated that patients with rare,
homozygous genetic defects in the melanocortin pathway
responded to set melanatide,
whereas broader patient populations
showed limited response.
The 2017 IPO Prospectus outlined a narrower commercial vision
than the company eventually pursued.
It contained no acquired hypothelamic obesity program,
no oral small molecule candidate,
and no dedicated sales force.
The molecule itself remains the primary link
between the company that listed in 2017
and the organization operating today.
What the early years say about the business?
Three operational characteristics established
during this period continue to define rhythm's strategy.
In licensing over internal discovery,
set melanatide came from Ipson,
delivery technology from Cameras,
and an oral small molecule was later acquired from LG Chem.
Only 718 originated in-house,
arriving more than a decade after founding.
Management's core focus has remained evaluating
and acquiring MC4R candidates
rather than maintaining an internal discovery engine.
Diversment over diversification.
The sale of Rella Morellen demonstrated a willingness
to sell non-core programs rather than build parallel
commercial teams across separate medical specialties.
Staged infrastructure deployment,
operating expenses in 2017 reflected a minimal cost structure
with SKND below $10 million and no field sales force.
Commercial infrastructure was deferred
until clinical labels were secured,
an approach that contrasts with the company's 2026 practice
of expanding commercial operations ahead of regulatory decisions.
The next four years would prove the science
and in the process expose an uncomfortable commercial truth.
On November 27th, 2020,
the FDA approved IMSIVRI, set melanatide,
for chronic weight management in adults
and pediatric patients age six and older with obesity
due to POMC, PCSK1, or leopard efficiency
confirmed by genetic testing.
Making it the first therapy ever approved
for those conditions.
The regulatory decision was supported
by substantial weight reductions in pivotal clinical trials.
Among patients with POMC or PCSK1 deficiency,
80% achieved more than 10% weight loss at one year,
while 45.5% of patients with leopard efficiency
met the same threshold.
In a therapeutic category where a 5% reduction in body weight
is typically considered clinically meaningful
and placebo control groups routinely gain weight,
the response rate in POMC and PCSK1 deficiencies
demonstrated that direct MC4R activation
could effectively bypass upstream genetic signaling blockades.
At the time of approval,
chief executive officer, Dr. David P. Meeker,
framed set melanatide as a first in class precision medicine
that is designed to directly address
the underlying cause of obesity's driven by genetic deficits
in the Melano-Cortin IV, MC4 receptor pathway.
That focus on correcting the underlying signaling deficit
rather than broadly suppressing appetite
became the core thesis of rhythms,
commercial and scientific model.
The commercial problem.
Initial commercial availability quickly revealed
a fundamental market challenge.
In 2021, its first full year on the market,
rhythm generated $3.2 million in product revenue
while incurring roughly $172 million in operating expenses.
This gap reflected the epidemiology of monogenic obesity
rather than commercial execution.
Identified patients with POMC, PCSK1,
or leopard deficiencies,
numbered in the low hundreds across the United States and Europe.
Even with an annual treatment cost near $300,000 per patient,
an ultra-rare indication with an unidentified patient base
could not generate sufficient revenue
to offset operating costs.
Rhythm had validated its drug's biological mechanism,
but it faced the hurdle of locating patients
scattered across global medical practices
who had never received genetic testing.
Building the funnel.
To address this diagnostic bottleneck,
rhythm developed a systematic patient identification strategy.
The company launched a sponsored genetic testing program
later branded uncovering rare obesity,
offering free panel testing through a CLIA certified laboratory
to patients with early onset severe obesity.
The panel eventually expanded to screen
approximately 80 obesity-related genes
far beyond the initial indications approved for imcivary.
This program was complemented by dedicated genotyping studies
and a global patient registry.
The initiative served three operational goals,
identifying actionable candidates for treatment,
mapping geographic and clinical clusters of diagnosed patients,
and educating treating physicians
that severe early onset obesity
could stem from identifiable genetic mutations.
However, genetic screening panels
remained commercially replicable by potential competitors.
Rhythm's primary operational advantage
lay in its accumulated clinical relationships
and medical network, as evidenced by its international team,
securing acceptance for 64 abstracts
across 12 scientific congresses in 2025 alone.
Widening the label, patient by patient.
Alongside diagnostic screening,
rhythm pursued incremental regulatory expansions
to broaden its addressable patient population.
European regulators authorized set melanetide for POMC
and leper deficiencies in 2021,
establishing an international channel
that Jan Mazabrod's team expanded across more than 25 countries.
In December 2024, the FDA lowered the minimum age threshold
from six to two years,
bringing younger pediatric patients facing severe,
lifelong hyperfagia into the treatable population.
These regulatory milestones allowed rhythm
to convert previously identified but ineligible patients
into active prescribers within its established medical network.
To support early intervention with payers,
rhythm collaborated with European medical experts
to publish a disease model in obesity facts,
integrating data from more than 140 publications
to demonstrate how early disease onset
and prolonged obesity accelerate comorbidity risk
and life expectancy.
The published analysis provided health economic arguments
for reimbursement authorities,
containing that early therapeutic intervention
reduces cumulative lifetime healthcare costs.
Ultimately, the diagnostic infrastructure
and physician network established
during the monogenic obesity launch
provided the operational blueprint for rhythm's subsequent growth.
The company developed a methodology
for identifying rare disease patients
within general clinical practice,
a capability that proved vital
when it pivoted toward acquired hypothalamic obesity,
an indication with a substantially larger target population.
In July 2020, four months before securing its initial FDA approval
and with its commercial organization,
still largely theoretical,
rhythm appointed a chairman, president,
and chief executive officer
with two decades of experience
navigating rare disease commercialization.
Whomaker is?
Dr. David P. Meeker is a pulmonologist by training
who spent much of his career at Genzyme,
the Cambridge company that established
the modern rare disease business model,
eventually serving as president and CEO of Santa Fe Genzyme,
following Santa Fe's acquisition.
That background is significant
because rare disease commercialization requires specialized execution
rather than broad primary care marketing.
Success depends on identifying key academic medical centers,
navigating complex prior authorization appeals,
establishing patient bridge programs during insurance transitions,
and compiling clinical evidence
that satisfies health technology assessment bodies.
Meeker adopted a cautious public stance.
On Rhythm's first quarter, 2026 earnings call,
following a launch quarter that exceeded expectations,
he remarked, "Launches are enormously challenging to forecast
and rare disease launches are even more difficult."
He consistently declined to provide explicit launch guidance,
establishing a track record of conservative communication
in an industry often prone to over-promising.
Meeker recruited senior leadership
with similar rare disease experience.
Jennifer Lee joined as executive vice president
and head of North America in November 2020
from Crystal Biotech,
where she served as chief commercial officer,
following five years at Santa Fe Genzyme,
including three as vice president
and head of genetic diseases.
Meanwhile, Jan Mazabrowd built an international team
of over 100 people across 13 countries by early 2026.
Bar-Date Beetle Syndrome.
The commercial inflection occurred on June 16th, 2022,
when the FDA approved IM-Kivri for obesity
in patients with Bar-Date Beetle Syndrome, BBS.
A genetic psiliopathy characterized by hyperphasia
and severe obesity alongside progressive vision loss,
renal dysfunction, polydactyly, and cognitive impairment.
The clinical trial evidence for BBS
demonstrated a lower efficacy threshold.
than observed in monogenic deficiencies.
In the pivotal study, 31 patients aged six and older
achieved an average 7.9% reduction in body mass index
at one year without diet or exercise requirements.
Compared to the 80% response rate observed
in POMC deficiency, this result illustrated
an essential biological principle.
As disease ideologies move further from clean,
isolated single gene defects in the melanocortin pathway,
the therapeutic impact of direct MC4R stimulation
becomes more diluted.
Notably, the FDA declined to approve
a companion indication in Alstrom syndrome
that rhythm had submitted concurrently
with the BBS application.
The regulatory process for BBS also encountered minor hurdles.
The FDA extended its review timeline in early 2022
prior to granting approval in June,
an operational delay that rhythm disclosed transparently
without attempting to reframe the narrative.
The argument that had to be won before the drug could be sold,
commercial success required overcoming
a standard payer response, classifying
M.Kivri as an elective weight loss treatment
and issuing automatic coverage denials.
Between 2022 and 2025,
rhythms primary commercial objective
was reframing MC4R pathway disorders
before utilization management committees.
The company argued that these conditions represent
distinct neuroendocrine diseases that manifest as obesity,
comparing set melanotide to targeted hormone replacement
therapy rather than general weight loss products.
This therapeutic positioning drove rhythms
substantial investment in medical congress presentations,
patient registries, and published disease models
to establish the evidentiary foundation required
for favorable coverage classifications.
In European markets, reimbursement hurdles
are structured formally rather than through individual payer
claims.
Germany's Federal Joint Committee
maintains an exclusion list barring coverage
for lifestyle drugs requiring rhythm
to secure specific regulatory exemptions
for each indication.
A process taking six to nine months that
must be repeated for acquired hypothalamic obesity.
Meanwhile, negotiations in France
resulted in an agreed reimbursed price
that required rhythm to record a one-time $3.2 million
revenue adjustment in the third quarter of 2025.
Consequently, rhythms' strong gross to net realization rate
is not an inherent feature of orphan drug pricing,
but the ongoing result of rigorous market positioning
that must be re-established across every new geographic
market and clinical indication.
The TAM math.
The approval in BBS expanded rhythms'
addressable patient population by approximately 10 fold,
with management estimating a US prevalence
of roughly 5,000 patients.
However, total epidemiological prevalence differs significantly
from the clinically diagnosed and accessible population.
Management acknowledged that during the initial commercial
launch, disease awareness and diagnosis rates were low.
What the revenue curve actually shows.
The commercial trajectory following the BBS approval
provides empirical evidence of rhythms' execution capabilities
across a complete product launch.
2021 $3.2 million 2022 $23.6 million
2023 $77.4 million 2024 $130.1 million 2025 $194.8 million
representing a 50% year-over-year increase.
Financial analysts interpret these numbers
through two distinct lenses.
The optimistic view highlights five consecutive years
of expanding revenue in an ultra-rare setting, demonstrating
that rhythms' patient identification model
can generate consistent commercial growth.
The cautious view emphasizes that annual growth rates
slowed from roughly 230% in 2023 to 68% in 2024
and 50% in 2025, with absolute annual additions
stabilizing near $65 million, indicating steady adoption
rather than rapid market saturation driven by overwhelming latent demand.
In practice, the BBS commercial rollout
reflected the typical dynamics of a relationship-intensive rare disease launch.
On the first quarter 2026 earnings call,
management characterized the experience candidly,
noting that it wasn't always easy, but we've learned from the challenges along the way.
The operational scaffolding.
Accompanying this top-line expansion rhythm established
its operational infrastructure, dedicated patient support services,
a bridge assistance program delivering free medication
to patients navigating insurance coverage delays,
and a payer education framework focused
on demonstrating therapeutic necessity.
Establishing that payer education framework
proved to be the most critical operational capability
developed during the BBS commercialization,
positioning the company for its subsequent expansion
into significantly larger patient populations.
Although cranioferingiomas are non-cancerous tumors
that do not metastasize, their location near the pituitary gland and hypothalamus
creates severe clinical complications.
As these tumors grow, they compress the neural structures governing endocrine function
and appetite regulation.
While surgical resection or radiation allows patients to survive the initial tumor,
it frequently damages or destroys hypothalamic tissue.
Patients often experience rapid and severe weight gain, gaining 50, 80, or 100 pounds,
because the neural hardware that processes satiety signals has been lost.
Standard medical care can replace thyroid, cortisol, and growth hormone deficiencies,
but clinical medicine historically lacked a therapy to restore satiety signaling.
That clinical deficit defines acquired hypothalamic obesity, HO.
Until March 2026, no regulatory authority had approved a targeted treatment for the condition.
Why this changed everything for rhythm?
The primary catalyst for rhythm is the expansion in addressable market size.
While Bardet Beetle Syndrome prevalence is measured in the low thousands,
acquired HO has an estimated target population of approximately 10,000 patients in the United States,
a comparable cohort in Europe, and 5,000 to 8,000 in Japan, where per capita prevalence is higher.
Equally critical is the structural difference in patient care.
On Rhythm's first quarter, 2026 earnings call, Chief Executive Officer Dr. David P. Meeker
described acquired HO as having a much more concentrated call point than BBS.
Because HO patients are survivors of brain tumors or hypothalamic trauma,
their long-term management is concentrated in specialized neurosurgery,
neurooncology, and pituitary centers.
Rhythm identified approximately 40 priority medical centers in the United States,
estimating that roughly one-third of the potential HO patients identified through claims data
were managed within those institutions.
In contrast to Bardet Beetle Syndrome, where patients are scattered across community medical practices,
the clinical concentration of acquired HO allows a specialized field force to cover the addressable
market efficiently. The evidence Phase 2, then Transcend
encouraging Phase 2 clinical signals prompted Rhythm to initiate its pivotal registration trial, Transcend,
which generated the central data set supporting the company's valuation.
Transcend randomized patients aged 4 and older, 2-to-1,
to daily sub-tutaneous set melanotide, or placebo, over 52 weeks.
In the primary analysis cohort of 120 patients,
set melanotide achieved a 16.5% mean reduction in body mass index, BMI,
compared to a 3.3% increase in the placebo group, yielding a placebo-adjusted reduction
of 19.8%, P80% of treated patients achieved at least a 5% BMI reduction.
When the full 142 patient data set was incorporated into the prescribing label,
the placebo-adjusted treatment effect was 18.4%, reflecting a 15.8% reduction in the treatment
arm compared to a 2.6% increase in the placebo group. The trial results were published in the
New England Journal of Medicine on July 8, 2026, with the senior author characterizing them as
a potentially transformative therapeutic advancement. The trial data highlights two important
clinical dynamics. First, control arm participants experienced continuous BMI gain over 52 weeks,
demonstrating the progressive nature of untreated disease. Second, the therapeutic response was
sustained over a full year across pediatric and adult cohorts, while discontinuation rates,
due to adverse events, remained comparable between the treatment and placebo groups.
However, long-term clinical evaluation must account for an open label extension design.
in a rare patient population alongside a recognized adverse event profile.
The prescribing information notes skin hyperpigmentation in a majority of clinical trial participants
and acute adrenal insufficiency in approximately 5%.
While efficacy evidence supported regulatory approval, the long-term tolerability of a daily
injectable in pediatric populations remains an active operational factor and a primary driver
of Rhythm's Pipeline Development, regulatory execution.
The FDA granted priority review for Rhythm's supplemental application, initially assigning
a prescription drug user fee-act action date of December 20, 2025.
Following a standard review extension to March 20, 2026, the agency approved IM-civory
for acquired HO on March 19, 2026.
European regulatory review proceeded faster than anticipated.
The committee for medicinal products for human use issued a positive opinion ahead of management's timeline,
and the European Commission granted marketing authorization in late April 2026.
Approximately four weeks after the recommendation compared to a standard two-month timeline.
In Japan, Rhythm implemented a direct regulatory and commercial strategy.
The company included a dedicated Japanese cohort within the Transcend trial, submitted a regulatory filing
to the pharmaceuticals and medical devices agency, established a 50-person in-country team,
and mapped 151 high-volume hospitals specializing in brain tumor surgery.
Management targeted Japanese regulatory approval within roughly one year of the U.S. decision.
A condensed timeline relative to the multi-year delays or regional licensing partnerships
typical of Western biotechs.
Efficacy in the Japanese cohort tracked the global trial population,
though the placebo-adjusted treatment effect was slightly narrower,
because Japanese placebo participants maintained stable BMI rather than gaining weight.
The launch, so far,
during the initial six weeks following FDA approval,
commercial launch metrics exceeded corresponding indicators
from the Bardet Beetle Syndrome launch across all disclosed parameters.
Rhythm received over 150 patient start forms,
including approximately 40 conversions from clinical trial participants.
These start forms originated from roughly 110 unique prescribers,
about 80% of whom were writing their first prescription for IM-civory,
with endocrinologists representing approximately 80% of the prescriber base.
Dr. Meeker noted that the rate of start forms in the first six weeks
is higher than we had in BBS, emphasizing broad market adoption.
This is not a launch where we've got two or three believers,
and they're writing a bunch of scripts.
Financial analysts focused on the durability of early demand.
Stifle analyst Paul Mateus questioned whether the initial intake rate
of roughly 20 patient start forms per week represented a temporary backlog
or a sustainable trend.
Jeffrey's analyst Dennis Ding examined potential operational barriers
preventing prescribers from issuing subsequent prescriptions,
while Goldman Sachs analyst Karin Johnson questioned the financial implications
of the initial payermix on net realized price.
Management addressed these inquiries qualitatively,
stating that prescription intake is governed primarily
by the scheduling cadence of specialist physician visits,
while noting that early payermix data remained preliminary.
Crucially, establishing formal HO-specific reimbursement policies
across commercial and government payers typically requires three to nine months post-approval.
Consequently, converting initial patient start forms into recognized commercial revenue
represents an extended trajectory spanning late 2026 into 2027,
rather than an immediate second quarter contribution.
Proportionality acquired HO represents the primary determinant
of rhythms forward valuation and commercial growth.
The company's major 2026 capital allocations directly reflect this prioritization,
expanding the North American sales force from 16 to 42 field representatives,
directing approximately 15% of incremental operating expenses
toward Japanese commercial infrastructure, and selecting acquired HO
for the Phase III clinical development of its investigational oral MC4R candidate.
With acquired HO established as rhythms primary commercial franchise,
the central strategic question facing investors is competitive durability
and franchise protection against emerging market entrants.
A core strategic vulnerability facing imsevery is not an increment in therapy,
but a potential oral therapy operating on the same biological mechanism.
A daily subcutaneous injection administered lifelong to a predominantly pediatric population,
causing skin hyperpigmentation in most patients.
Presents an attractive target for competitive displacement.
An oral MC4R agonist achieving comparable clinical efficacy could capture significant market share.
To address that threat, rhythm moved to acquire its primary oral competitor.
The LG Chem Deal.
On January 4th, 2024, rhythm announced an exclusive license agreement
with LG Chem Life Sciences for worldwide rights to buy Vamellagon,
LB54640, an investigational oral small molecule MC4R agonist then in Phase II development.
Under the deal terms, rhythm agreed to pay $40 million in upfront cash
and approximately $20 million in common stock at closing.
Followed by $40 million in cash 18 months later,
plus up to $205 million in potential development and commercialization milestones alongside tiered royalties.
Korean media valued the total package at up to $305 million.
Rhythm also assumed sponsorship of two ongoing clinical trials.
Signal, a randomized placebo-controlled Phase II study in roughly 28 patients with acquired hypothalamic obesity,
and route, an open-label study evaluating POMC, LEPR, or PCSK1 deficiency.
Evaluating this transaction depends more on what it neutralizes than what it immediately adds.
By committing roughly $100 million in near-term upfront consideration, half in stock,
rhythm acquired the primary external threat to its commercial franchise before Phase II data could escalate the assets valuation.
Preemptive self-disruption is rare in commercial biotechnology,
as it requires management to acknowledge the structural vulnerabilities of its primary marketed product.
Did it work?
Initial clinical results validated the asset, though regulatory requirements introduced operational complications.
Phase II top-line data released on July 9, 2025 demonstrated that BIVA MELEGON achieved mean body mass index reductions of 9.3% in the 600-mg cohort,
and 7.7% in the 400-mg cohort at 14 weeks, with a mean 2.8-point reduction in hunger scores across both groups,
and limited instances of localized hyperpigmentation.
Rhythm's share price rose following the data release.
Subsequent open-label extension data showed sustained responses at 6 and 9 months, reaching an 18.9% mean BMI reduction among the 11 participants followed longest.
However, regulatory requirements altered the development timeline.
During its end of Phase II meeting with the FDA, Rhythm sought a six-month double-blind trial period and a smaller patient sample,
arguing that prior set melanetide studies and historical placebo data in acquired hypothalamic obesity established baseline disease progression.
On the fourth quarter 2025 earnings call, Dr. Meeker reported that the FDA required a complete 12-month double-blind, randomized controlled trial
in a larger patient population expected to approach the 142 patient sample size of the set melanetide pivotal study.
This requirement expanded both the financial budget and development timeline for the program.
Additionally, trial compliance data revealed pediatric administration challenges as younger adolescent participants struggled to swallow the initial pill formulation.
In response, Rhythm initiated development of a redesigned single tablet formulation for each dose alongside a chewable option for younger pediatric patients.
Rhythm targets Phase III initiation in acquired hypothalamic obesity by late 2026, with bio-equivalence, drug-drug interaction, and hepatic impairment studies running first.
Management plans to conduct the pivotal trial primarily in international jurisdictions where set melanetide is not yet commercially available,
reflecting the operational reality that enrolling patients into a placebo-controlled trial becomes difficult once an approved therapy is established in a given market.
RM718, the in-house hedge.
The second defense strategy relies on internal development. RM718 is an investigational week
specifically MC-4R specific peptide engineered to avoid binding MC-1R receptors.
Specifically designed to eliminate the skin hyperpigmentation associated with
set melanetide. Initial clinical trial dosing began in a three-part phase one
study in March 2024, progressing from healthy volunteers to multiple ascending
doses in patients with hypothalamic obesity. By 2026, the program had expanded
into Prada-Willy syndrome, with Part C, hypothalamic obesity data targeted
around mid-year. These pipeline initiatives represent substantial capital
commitments. Approximately 30% of rhythms 104.5 million dollar projected
increase in planned 2026 operating expenses was allocated to formulation,
manufacturing, and clinical supply for bivomelagon and RM718 combined. The
form factor thesis, tested, rhythms portfolio strategy aims to control a daily
injectable, a weekly injectable, and a daily oral formulation. The primary
delivery mechanisms through which a competitor might enter the market. However,
owning three investigational assets does not equate to absolute market
exclusivity over the MC-4R target. Two of rhythms pipeline candidates remain
unproven in pivotal phase three trials, and patent claims around a biological
receptor do not prevent alternative scientific approaches. Rather than
establishing permanent market ownership, rhythms pipeline investments have
secured commercial time and strategic optionality. A position that remains
contingent on bivomelagon demonstrating efficacy and safety in a 12-month
pivotal trial. Pulling the geography back in-house, in parallel with pipeline
expansion, rhythm began consolidating its global commercial rights. In March 2025,
the company re-acquired commercial rights to IMCIVRE in mainland China, Hong
Kong, and Macau, by terminating its 2021 licensing agreement with
Rairstone Group Limited, returning the equity shares it had received from
Rairstone for no additional financial consideration. While modest in financial
scale, the transaction indicated a strategic shift toward internalizing
commercial operations in international markets to capture full gross margins.
This direct commercial approach parallels rhythms expanded infrastructure
investment in Japan. Whether this strategy yields superior long-term
returns depends on commercial execution, an operational challenge directly
reflected in the company's financial performance, stripped of its biological
complexity, rhythm operates on a straightforward financial model. A single
commercial product sold to a few thousand rare disease patients at a premium
price, yielding high gross margins, funded primarily through equity, and yet to
achieve profitability. Where the revenue comes from? In the first quarter of
2026, global net product revenue reached 60.1 million dollars, with 36.9
million dollars, or 61 percent, originating in the United States, and 23.2
million dollars from international markets. Geographic distribution has
gradually shifted. In the fourth quarter of 2025, the US accounted for 68
percent of 57.3 million dollars in net sales. International momentum
accelerated in early 2026, with ex-US revenue expanding 27 percent
sequentially in the first quarter, propelled by commercial expansion in
Germany and France, alongside named patient sales in countries such as Saudi
Arabia and Greece. IMCIVRE is now commercialized across more than 25 countries
outside the US. However, named patient sales fluctuate significantly due to
irregular ordering patterns and extended lead times. A dynamic management
explicitly cited as a driver of quarterly revenue volatility.
Consequently, single quarter international performance may not reflect long-term
run rates. By clinical indication, revenue remains predominantly driven by
Bardet-Beetle syndrome, supported by a modest, consistent baseline from the
monogenic POMC, PCSK1, and LEPR deficiencies. Acquired hypothalamic obesity
generated minimal revenue in the first quarter of 2026, as FDA approval
occurred just 12 days before the close of the period. The revenue
recognition texture. Two operational disclosures clarified the
distinction between product shipped to distributors and product actively
dispensed to patients. First, specialty pharmacy inventory levels expanded
to approximately 20 days on hand at the end of 2025 compared to a baseline
range of 10 to 15 days. A build-up management caution would create a revenue
pull forward and slow subsequent growth. That dynamic materialized in the first
quarter of 2026. Sequential revenue grew by just 5% even as the global count of
patients on reimburse therapy expanded by 8%. Second, annual insurance plan
transitions each January temporarily shift a subset of patients onto Rhytham's
free drug bridge program. This seasonal transition occurred in both 2025 and
2026. Temporarily suppressing first quarter recognized revenue relative to
actual patient demand. As a result, total reimbursed patient count provides a
clearer indicator of underlying commercial demand than reported quarterly
revenue. Management's early disclosure of inventory fluctuations offered
transparent visibility into these short-term revenue discrepancies before they
impacted financial reporting. Unit economics. Rhytham maintains favorable
product level unit economics. Gross margins remain near 90% after accounting for
manufacturing costs and the ongoing Ipsin royalty, while the gross to net
realization rate holds near 84%, an exceptionally high level of price
retention for a specialty therapeutic. However, robust product margins have
not translated into bottom line profitability due to a lack of operating
leverage. The cost-base. In the first quarter of 2026, research and development
expenses reached $41.7 million, while selling, general, and administrative,
Escanda, expenses rose to $63.6 million, against $60.1 million in total product
revenue. Escanda spending alone exceeded top-line revenue, climbing 63% year
over year as the company expanded commercial headcount and initiated launch
marketing for acquired hypothalamic obesity. Full-year 2026 guidance
anticipates non-gap operating expenses between $385 million and $415 million
divided roughly equally between R&D and Escanda. This represents an annual
expense increase of approximately $104.5 million, or 35% over the $295.5 million
recorded in 2025. Management attributed roughly 30% of this budget
expansion to manufacturing and formulation for next-generation compounds,
25% to US commercial infrastructure for hypothalamic obesity,
and 15% to establishing operations in Japan. Equity Delusion also represents a
substantial portion of reported operating costs. Stock-based compensation
totaled $66.8 million out of $362.3 million in gap operating expenses for 2025,
and reached $23.1 million in the first quarter of 2026,
accounting for approximately 22% of total reported operating expenses for the
quarter. The balance sheet. Rhythm closed the first quarter of 2026
with approximately $340.6 million in cash, cash equivalents, and short-term
investments, down from $389 million at year end 2025,
which management projects will fund operations for at least 24 months.
The company's capital structure also reflects ongoing preferred stock
conversions. In April 2024, rhythm raised $150 million in gross proceeds
through convertible preferred shares that accrued dividends and convert into
equity over time. By February 2026, conversions representing nearly
25% of the initial preferred shares had taken place, reducing dividend
obligations while expanding the common share count to $68,285,000 and 39 shares
as of February 24th, 2026. Throughout its history, rhythm has relied
exclusively on equity financing rather than debt, funding growth through its IPO,
follow-on offerings, preferred equity issuances, and stock consideration for the
LG Chem license. While issuing equity avoids debt service obligations for an
unprofitable business, total shares outstanding roughly doubled
between 2020 and 2026. With a projected 24-month cash runway,
future equity delusion remains an active consideration for investors.
What the financials actually say. Rhythm has demonstrated that it can commercialize
an ultra-rare disease therapy at a premium price,
maintain high gross margins, and deliver steady revenue growth over five years.
However, the company has not yet demonstrated that it can achieve the operational
scale required to cover an expense structure that management is deliberately
expanding by 35% in a single
year.
This spending reflects a clear strategic wager, that market expansion in acquired hypothelamic
obesity and entry into Japan will generate a revenue base large enough to justify its
enlarged commercial and clinical infrastructure.
If initial prescription intake converts into recognized revenue at the pace observed in
the first six weeks post-approval, that strategy appears viable.
Conversely, if insurance coverage delays or reimbursement hurdles slow conversion,
Rhythm's medium-term trajectory will once again center on capital raising,
stripping Rhythm's corporate history down to transferable lessons yields four core insights
for bio-farmist strategy and investing.
One, define the disease, not the symptom, then price accordingly.
Rhythm's founding asset was a general obesity candidate that a large European pharmaceutical
firm willingly licensed at minimal upfront cost.
Its commercial value was unlocked through progressive narrowing, moving from general obesity
to rare monogenic deficiencies, then to specific pathway defects and ultimately to physical
structural destruction of hypothelamic tissue.
Each narrowing reduced the target patient population, while increasing the asset's clinical
necessity and unit economics.
That inversion holds only when a narrow patient cohort possesses three attributes, a clear
diagnostic boundary, an absence of therapeutic alternatives, and a regulatory and payer consensus
treating the condition as a distinct disease rather than an elective lifestyle issue.
Rhythm fought all three battles.
The reimbursement classification fight is often underestimated by developers because
it must be secured before initial commercial prescriptions can be written and systematically
re-established across each international jurisdiction.
The broader strategic lesson is not merely to target rare diseases.
It is that the boundaries separating a fully reimbursed neuroendocrine disorder from
an unreimbursed lifestyle condition is a strategic variable a company can actively shape,
a multi-year campaign rather than a post-approval launch tactic.
Two, buy the thing that would have killed you.
The LG Chem Transaction stands as a notable example of a biotech acquiring its primary
competitive threat while the asset remained relatively early in development.
The discipline required was as much psychological as financial.
By acquiring by Vamellagon, management implicitly acknowledged that the daily injectable format
it was preparing to launch into its largest market represented a transitional therapy.
Few commercial incumbents willingly pursue self-disruption.
For investors, the crucial question is whether rhythm can maintain that strategic posture
when by Vamellagon reaches market and begins actively cannibalizing im-civary revenue rather
than merely serving as a defensive pipeline hedge.
Three, diagnostic infrastructure is distribution.
In an underdiagnosed condition, the primary commercial bottleneck is neither manufacturing
supply nor pricing power, but patient identification.
Problems sponsored genetic testing programs, global registries, medical congress presence,
and claims data analytics are not auxiliary marketing tactics.
They function as the company's core distribution infrastructure.
That operational dynamic was evident in the acquired hypothalamic obesity launch.
Management noted that the vast majority of early patient start forms originated from physicians
the field team had engaged prior to regulatory approval, with rhythm having built relationships
with clinicians managing over 2,000 diagnosed or suspected hypothalamic obesity patients
ahead of the FDA decision.
A rapid commercial trajectory in rare disease is rarely spontaneous.
It represents the realization of multi-year preparatory work.
However, diagnostic infrastructure carries a structural limitation.
Awareness depreciates as a proprietary asset.
Since treating physicians are educated on diagnosing pathway disruptions, that clinical awareness
inherently lowers market entry hurdles for future MC4R competitors.
Rhythm built market awareness, but it cannot patent physician education.
Four, match the executive to the stage.
The early iteration of rhythm, 2008/2019, required leadership adept at opportunistic in licensing
and cost-effective clinical development.
Reaching commercial scale from 2020 onward demanded a distinct skill set, executives experienced
in negotiating with international health authorities, establishing specialized field forces,
and navigating complex rare disease reimbursement frameworks.
Recognizing that operational transition, rhythm recruited leadership from Santa Fe Genzai,
an organization with extensive experience in rare disease commercialization.
That background is reflected in management's operational approach, a disciplined tolerance
for extended launch trajectories, a deliberate refusal to issue speculative revenue guidance,
and a willingness to invest heavily in payer education long before regulatory approvals materialize.
However, that rare disease commercial model presents a clear financial trade-off, establishing
specialized global infrastructure ahead of revenue generation, drives selling, general
and administrative expenses elevated relative to near-term sales, creating the substantial
cost structure that defines Rhythm's 2026 financial profile.
This strategic framework leads directly to the central debate surrounding Rhythm's enterprise
valuation, myth versus reality.
Myth, rhythm holds an absolute monopoly on the MC4R pathway, reality.
Rhythm holds the only regulatory approved MC4R agonist, orphan exclusivity across its
indications, and the two most advanced next-generation candidates in development.
While this represents a formidable commercial lead, it is bounded by statutory exclusivity
periods, rather than permanent ownership of a biological target.
Management's capital allocation.
Specifically committing nine figures to acquire an external oral compound demonstrates
an internal recognition that the current commercial position requires active defense.
Myth, Incretan therapies present in immediate competitive threat across all target indications.
Reality, Incretan therapies are largely ineffective in addressing severe structural damage
to hypothalamic tissue, which defines the primary acquired hypothalamic obesity population.
However, their potential utility at the boundaries of the label, where hypothalamic function
is partially impaired rather than fully destroyed, or in mild genetic variance, remains less defined
as no randomized head-to-head clinical trials exist.
Myth, The MC4R mechanism is broadly effective across all melanocortin pathway disorders.
Reality, Clinical trial results in early 2026 defined the operational limits of direct
receptor stimulation.
In the Phase 3 Mn8 trial, all four substudies failed to meet their primary efficacy endpoints.
heterozygous POMC/PCSK1 variants showed a placebo-adjusted body mass index reduction of
minus 4.3 percent, P=0.15.
Lepper heterozygous reached minus 3.6 percent, P=0.94, SRC1 reached minus 4.0 percent, P=0.12,
and SH2B1 reached minus 1.7 percent, P=0.43.
Retrospective subgroup analyses indicated statistical significance in select patient subsets,
though post-hoc findings carry limited regulatory weight.
These trial outcomes established a clear biological boundary.
Set melanotide demonstrates consistent clinical efficacy where signaling is structurally
or genetically disrupted, but shows inconsistent results where pathway function is merely impaired.
Rhythm strategy of directing these patient populations toward next-generation candidates
and expanded genetic characterization converts a near-term commercial expansion into a multi-year
development effort.
Interim clinical data in Prader-Willie syndrome revealed similar therapeutic boundaries.
Prior to data release, management outlined a public efficacy threshold on its fourth
quarter 2025 call, targeting a body mass index reduction exceeding 5 percent.
Six-month interim data presented at the Endo 2026 conference demonstrated a 3.11 percent
mean reduction in adult participants, N=sign 10, and a 3.00 percent reduction in pediatric
participants, N=sign 7.
Although the trial demonstrated secondary improvements in hyperfagia scores, body composition,
and food-related anxiety with high-participant retention, 17 of 18 patients remaining
on therapy, primary weight reduction fell short of management's benchmark.
Furthermore, entering the Prader-Willie market requires competing against Selenotherapeutics
VYKATXR, which received FDA approval for Prader-Willie hyperfagia in March 2025.
Management's predeclaration of a numeric benchmark prior to reporting data that fell short provides
The Transparent Disclosure Board.
baseline. Hamilton Helmer's seven powers applied, honestly,
cornered resource. Present, representing the primary competitive driver.
Rhythm maintains the only approved MC4R agonist, orphan designations,
10 years of pathway safety data, and a pivotal data set in hypothelamic obesity
published in the New England Journal of Medicine. Although statutory exclusivity
is finite, replicating this clinical evidence in ultra-rare populations
represents a significant operational hurdle for potential competitors,
who would face ethical and enrollment barriers, conducting placebo-controlled
trials against an established standard of care,
process power, present but modest. The patient identification and diagnostic
infrastructure required seven years to construct. While functional,
these networks are conceptually replicable by well-capitalized market
entrants. Counter-positioning. Week, large pharmaceutical companies
face no structural disincentive to target pediatric
endocrinology markets. Rather, they prioritize larger commercial opportunities.
This reflects resource allocation strategy rather than a business model conflict.
Scale economies, network effects, switching costs, branding,
largely absent. Manufacturing scale provides minimal margin advantage at rare
disease volumes, and network effects do not apply.
Patient-level switching costs stem primarily from clinical inertia.
As patients experiencing hyperphasia relief are hesitant to alter effective
regimens. Rather than contractual lock-in, a bio-equivalent oral alternative
demonstrating comparable efficacy could navigate these clinical barriers.
In summary, rhythms' mode relies on one primary power and one secondary power.
The competitive barrier is narrower than a monopoly framing suggests,
explaining management's focus on securing alternative delivery
formulations. Porter's five forces,
new entrants, low to moderate. Technical challenges in achieving
MC4R selectivity, without cardiovascular toxicity,
combined with orphan exclusivity and published pivotal data,
present high entry barriers. However, by Vamelegon demonstrated that external
developers can successfully engineer oral candidates.
Rhythm neutralize that competitive threat through acquisition,
but acquiring every emerging candidate is financially unfeasible.
Firepower, moderate and rising. US payers have maintained high gross
to-net realization rates for established indications,
but coverage policies for acquired hypothalamic obesity remain in development.
European health systems enforce strict formal price negotiations,
resetting reimbursement terms across every new indication.
With European launches anticipated to begin in 2027,
national reimbursement terms negotiated over the next 18 months
will establish international margin ceilings for the franchise.
Substitutes
Low in core hypothalamic obesity
bariatric surgery and in-cretan therapies have demonstrated minimal efficacy
in patients with severe structural hypothalamic damage,
making substitution risk lowest in this core indication.
rivalry low currently structurally rising.
No approved competitor exists in acquired hypothalamic obesity,
though competitive density in adjacent rare metabolic indications is increasing.
Supplier power low with one exception.
Ipsin's perpetual royalty structure on set melanotide
represents a permanent deduction from gross margins.
The activists stress test.
An institutional evaluation highlights four operational risks.
Operating expense growth ahead of revenue conversion.
Guiding to a 35% increase in annual operating expenses
while declining to provide explicit commercial launch guidance
represents aggressive capital deployment.
The commercial infrastructure expansion in Japan,
comprising roughly 50 personnel and 15% of incremental operating spend,
commits capital ahead of final regulatory decisions.
Equity dilution history.
Cumulative equity issuances across the initial public offering,
follow-on rounds, a $150 million convertible preferred financing,
and license consideration paid to LG Chem
have expanded total share count.
Ongoing conversions of preferred shares continue to add to the common equity supply.
Single asset concentration.
Product revenue depends entirely on set melanotide.
While Bivemelegon and RM718 mitigate delivery format risks,
they rely on the same biological mechanism,
leaving the franchise vulnerable to pathway-level safety signals.
Disclosure metrics.
Disclosure's emphasized patient start forms, prescribing physician counts,
and reimbursed patient totals, while omitting absolute active patient counts,
net-realized price per patient, and real-world discontinuation rates.
In a daily injectable therapy associated with widespread skin hyperpigmentation,
long-term adherence rates remain a critical missing metric.
Conversely, management has demonstrated operational consistency,
providing advanced notice of inventory adjustments,
reporting clinical trial misses transparently,
communicating FDA Phase III trial requirements for Bivemelegon directly,
and securing regulatory approval for acquired hypothalamic obesity
on its designated action date.
Bull case.
Acquired hypothalamic obesity commercialization
maintains its initial trajectory.
US revenue accelerates through 2026 and 2027,
as formal payer policies are established.
European launches commence in 2027,
following price negotiations,
and Japanese regulatory authorization leads to a 2027 commercial rollout.
Operating leverage emerges as top-line growth absorbs pre-built commercial infrastructure.
Bivemelegon successfully completes Phase III testing,
enabling Rhythm to transition the franchise to an oral formulation.
Consequently, Rhythm becomes a strategic acquisition target
for larger bio-pharmaceutical firms seeking established rare disease commercial operations.
Bear case.
Initial patient start forms reflect a transient backlog of diagnosed cases
with prescription intake normalizing at lower levels.
Payers implement restrictive prior authorization criteria,
requiring documented surgical injury,
failed-step therapy,
or strict body mass index thresholds,
limiting commercial access.
Administration burden and skin hyperpigmentation drive real-world treatment
discontinuation above clinical trial rates.
European pricing negotiations result in lower net realization,
while annual operating expenses near $400 million outpace revenue growth,
forcing additional equity capital raises.
Bivemelegon's expanded 12-month Phase III trial delays commercialization,
allowing competitive oral assets to advance.
M&8 and Prader-Willie trial results
established the definitive limits of the mechanism,
capping the addressable market at hypothalamic obesity and Bardet Beetle syndrome.
The three KPIs that matter.
1. Reimbursed patient count segmented by US and international markets.
Reimbursed patient totals provide a clearer demand signal than quarterly product revenue,
which is subject to specialty pharmacy inventory fluctuations
and seasonal insurance reauthorization cycles.
2. Prescriber adoption and repeat prescription volume in hypothalamic obesity.
Tracking unique prescribers alongside repeat prescription activity
clarifies whether commercial adoption reflects broad clinical utilization
or concentrated initial intake.
3. Phase III execution for Bivemelegon.
Initiating the pivotal trial by late 2026 and maintaining enrollment timelines
across the 12-month double-blind study of approximately 142 patients
will determine whether rhythm can execute its life cycle defense strategy.
Rhythm successfully validated a targeted therapy
in an unaddressed rare disease and secured broad regulatory approval.
The company's forward valuation depends on demonstrating that its commercial
infrastructure can achieve profitability across its target patient population.
This podcast is brought to you by impor.top, the stories of top companies.
If you like our podcasts, please subscribe on Apple podcasts, Spotify,
or your favorite podcast player, and don't forget to follow us on X at impor.top.
Find thousands of stories of top companies on our website, impor.top.
Impor.top is brought to you by hayfin.co.
Podcast Summary
Key Points:
Rhythm Pharmaceuticals built a commercial monopoly around the MC4R pathway by targeting rare, genetically driven obesity conditions where existing therapies fail.
The company secured its first regulatory approval for a rare genetic disorder in 2020, followed by expansion into acquired hypothalamic obesity, a significantly larger patient population.
A core commercial strategy involves patient identification through diagnostic programs, medical network expansion, and payer education to establish disease-specific reimbursement.
Rhythm’s financial model relies on high gross margins and premium pricing, but it remains unprofitable due to high R&D and commercial expenses.
The company acquired its primary competitive threat, an oral MC4R agonist from LG Chem, to preempt market entry and protect its injectable franchise.
The success of Rhythm’s commercial strategy hinges on overcoming payer resistance and maintaining patient adherence in a condition driven by chronic physiological needs.
The company’s entire value proposition is built on a narrow, underdiagnosed patient population, making it vulnerable to market shifts and pricing pressures.
Rhythm’s long-term viability depends on proving sustainable commercial execution, not just scientific validation of its mechanism of action.
Summary:
Rhythm Pharmaceuticals has established a niche in the rare disease space by targeting obesity caused by disruptions in the melanocortin IV (MC4R) receptor pathway. Its flagship therapy, imcivry, received FDA approval for rare genetic disorders like POMC and PCSK1 deficiencies in 2020, and later for acquired hypothalamic obesity in 2026, expanding its addressable market from a few hundred to tens of thousands of patients globally. The company’s strategy hinges on identifying patients through diagnostic programs, building strong physician and medical center relationships, and securing payer reimbursement by framing the condition as a distinct neuroendocrine disease rather than elective weight loss.
Despite strong gross margins—nearly 90% and a high gross-to-net realization rate of 84%—Rhythm remains unprofitable, with operating expenses rising 35% in 2026 due to expanded commercial and clinical infrastructure. A key defensive move was acquiring LG Chem’s oral MC4R agonist to preempt competitive displacement. Additionally, Rhythm is developing a next-generation peptide (RM718) to eliminate skin hyperpigmentation and a new oral formulation to diversify its pipeline.
However, the path to profitability is uncertain, as revenue growth depends on patient conversion rates, reimbursement timelines, and sustained payer acceptance. Investors must assess whether Rhythm can maintain its commercial moat in the face of broader market competition, operational complexity, and the inherent challenges of ultra-rare disease commercialization. The company’s success underscores that rare disease value is not just in science, but in diagnosing, managing, and positioning a disease as medically necessary—work that requires long-term, relationship-intensive execution.
FAQs
Rhythm Pharmaceuticals targets the MC4R pathway to treat rare forms of obesity caused by genetic or structural disruptions in the hypothalamus, offering a precision medicine solution that restores satiety signaling.
While GLP-1 therapies act upstream in appetite regulation, Rhythm's drug directly activates the MC4R receptor, making it effective for patients with disrupted hypothalamic signaling due to tumors, surgery, or genetic defects.
The company faces challenges in identifying rare patients with acquired hypothalamic obesity, as the condition is underdiagnosed and scattered across multiple medical specialties with no standardized diagnostic coding.
Rhythm maintains a high gross-to-net realization rate of around 84%, indicating strong pricing power and payer acceptance, despite not yet achieving profitability.
The company gained FDA approval for Bardet-Béti syndrome and later for acquired hypothalamic obesity in 2022 and 2026, respectively, based on strong clinical data showing significant weight reduction in affected patients.
Rhythm has acquired an oral MC4R agonist from LG Chem and is developing a new weekly peptide (RM718) to avoid skin hyperpigmentation, both to protect its commercial position in a high-risk market.
Chat with AI
Loading...
Pro features
Go deeper with this episode
Unlock creator-grade tools that turn any transcript into show notes and subtitle files.
 PodcastTranscript AI